Why Traditional Flap Dissection Is Traumatic
If you’ve ever wondered why some surgeries feel “more intense” afterward than others—even when the goal is similar—the answer often comes down to how much tissue is cut, lifted, and held under tension during the procedure. One of the biggest drivers of early discomfort is traditional flap dissection, a long-standing surgical method used across many fields to improve visibility and access.
Below is a patient-friendly breakdown of what traditional flap dissection is, why it can create more surgical trauma, and how less disruptive approaches (including some minimally invasive septoplasty concepts) aim to reduce early inflammation and recovery burden in selected cases.
A helpful way to think about it: surgery isn’t only about what gets corrected (bone, cartilage, or alignment). It’s also about how much the “covering layer” has to be moved around to reach the target. That “covering layer” is often where much of the swelling and soreness comes from early on.
Quick take: what “traditional flap dissection” means (and why it matters)
Definition in plain language
A “flap” is a section of lining tissue that’s cut and lifted so the surgeon can work on the underlying framework (often bone or cartilage). After the work is done, the tissue is repositioned and sutured back into place. This “incise → lift → work → replace” pattern is a core feature of traditional flap dissection. [StatPearls, 2024]
A concrete analogy
Imagine lifting up a corner of carpet to fix something underneath. Even if you do it carefully, the carpet edge gets bent, pulled, and stressed—and then it has to be laid back down and re-secured.
Why patients notice the difference
From a recovery standpoint, more cutting + lifting + stretching usually means:
• more early inflammation
• more opportunities for bleeding or oozing
• a larger area the body must repair
That’s why traditional flap dissection often correlates with more noticeable early symptoms (like tenderness and swelling), even when long-term outcomes can still be excellent. Many clinicians summarize it this way: the more tissue you ask the body to “re-glue,” the more your immune system shows up to manage the repair.
About the evidence scope
This article uses general tissue-handling principles from flap biology (including oral and periodontal literature) to explain why flap elevation can increase early inflammation. Those data illustrate mechanisms and trends but are not direct nasal-surgery outcomes; anatomy and healing differ by site. Procedure-specific decisions should rely on nasal data and your surgeon’s judgement.
Bottom line: tissue principles are shared, but numbers and risks don’t copy‑paste across body sites.

What happens during traditional flap dissection (step-by-step)
1) Incision (cutting through the lining)
An incision creates the entry point. It also triggers the body’s normal healing response: inflammation, clotting, and immune activity at the wound edges. [StatPearls, 2024] Even in a clean, controlled surgical setting, the body interprets an incision as an injury that needs a coordinated repair response, which creates early warmth, throbbing, and swelling.
2) Elevation/reflection (lifting tissue off underlying framework)
Next comes flap elevation—the tissue is mechanically separated from what it normally adheres to. Even with meticulous technique, lifting tissue introduces stress: pulling, stretching, and micro-injury that can contribute to soreness and swelling afterward. [StatPearls, 2024]
3) Separation from the supportive layer (periosteum/perichondrium concepts)
In many parts of the body, the lining tissue closely associates with supportive layers that nourish healing. Elevating a flap separates these layers and can transiently alter the biologic environment above and below—so the body must re-establish stability and micro-circulation over a wider area, not just at the incision line. [StatPearls, 2024]
4) Retraction (holding the flap out of the way)
To maintain visibility, retractors hold the flap back. Pressure and time under retraction can add irritation and swelling. [StatPearls, 2024]
5) Closure and suturing (putting the flap back)
Finally, the flap is repositioned and sutured. Sutures and wound-edge tension can contribute to tenderness and, sometimes, healing challenges. [StatPearls, 2024]
In short, incising, lifting, retracting, and suturing create a predictable early inflammatory burden the body must resolve.

The biggest biological reason it can be traumatic: temporary blood-supply disruption
Flap elevation can reduce blood supply—temporarily
When tissue is elevated, some small vessels that contribute to local perfusion may be stretched, compressed, or interrupted—at least for a period of time. [StatPearls, 2024] Even when the flap heals well, temporarily reduced blood flow can mean more early inflammation while the body manages repair and re-perfusion.
Why reduced blood flow matters
Blood flow delivers oxygen, nutrients, and immune support. When perfusion dips, it can contribute to:
• hypoxia/ischemia
• slower early healing
• tissue edge vulnerability (in severe cases, tissue necrosis)
• remodeling changes in supportive structures
What research in flap biology shows
Studies of surgically created defects document measurable healing and dimensional changes in elevated supportive layers—evidence that flap elevation is not biologically “neutral,” even with careful technique. [Cho 2011]
Think of blood flow as the delivery truck for healing; if deliveries slow briefly, early recovery can feel rougher even when long-term results are good.

How “trauma” shows up after surgery (what patients may feel or see)
Common early symptoms
After traditional flap dissection, common early symptoms may include:
• tenderness or pain
• swelling and pressure
• bleeding/oozing
• sensitivity around the treated area
• discomfort that peaks in the first few days and then gradually improves
These are expected consequences of tissue manipulation and the inflammatory response—not signs that the surgery “failed.”
Wound-healing issues that can happen
Most patients heal uneventfully, but surgical literature recognizes potential issues influenced by tissue handling and closure tension, such as:
• wound separation (dehiscence)
• infection risk (variable by site/procedure)
• scarring changes
• delayed healing
Complication tracking in published flap-surgery data
Rates vary widely by procedure, anatomy, and patient factors. For example, one periodontal flap study reported sensitivity (10.74%), swelling (9.92%), pain (7.44%), and delayed healing (4.13%). [Gu 2025] Because this is oral/periodontal surgery, those percentages should not be assumed to apply to septoplasty; they simply illustrate that soft‑tissue manipulation often leads to real, trackable patient experiences. Pain guidance across specialties also notes that early discomfort correlates with the degree of tissue injury and inflammation. [CDA, 2013]
Early swelling and soreness usually reflect how much tissue was handled more than how “successful” the correction was.

Why sutures, flap tension, and retraction can increase risk
More edges to heal
Longer or more complex incisions create more wound perimeter to repair. [StatPearls, 2024]
Closure tension can work against healing
If a flap is closed under higher tension, it may feel more sore, swell more, and be more prone to wound-edge stress. Surgeons aim for tension-free closure, but anatomy and goals can limit that. [StatPearls, 2024]
Retraction pressure adds another layer of injury
Retraction is necessary for visibility, but pressure plus time can irritate tissue—one reason gentle handling and efficient steps matter. [StatPearls, 2024]
Good outcomes depend on what is corrected and how respectfully the soft tissue is treated along the way.
Are “flapless” or minimally invasive approaches less traumatic?
What studies generally find
Across multiple fields, a flapless or reduced-flap approach is often associated with:
• less surgical trauma
• lower early postoperative pain
• more favorable initial soft-tissue healing
• sometimes less marginal bone change early on
However, long-term hard-tissue outcomes are not uniformly better in every study or indication. [Jain 2024] For an overview of minimally invasive approaches that reduce surgical trauma, see less surgical trauma.
Less early trauma can be a meaningful patient benefit, but it doesn’t automatically guarantee superior long-term anatomy.
Why flapless isn’t always the right choice
Visibility and access matter. Some anatomy or goals require direct exposure, complex correction, or management of variations. In those cases, traditional flap dissection may still be the safest, most effective route.
A practical balance: minimize disruption when you can do so safely; prioritize exposure when precision and safety require it.
Connecting the concept to nasal surgery: reducing or avoiding mucoperichondrial flap elevation
Why nasal lining preservation is a big deal
Inside the nose, the lining tissue is delicate and reactive. When procedures reduce cutting and lifting, they may reduce early inflammation for some patients—potentially leading to less early swelling, pain, and congestion. Learn more about reducing flap elevation in nasal surgery here: reducing flap elevation.

A minimally invasive example: balloon-assisted septoplasty concepts
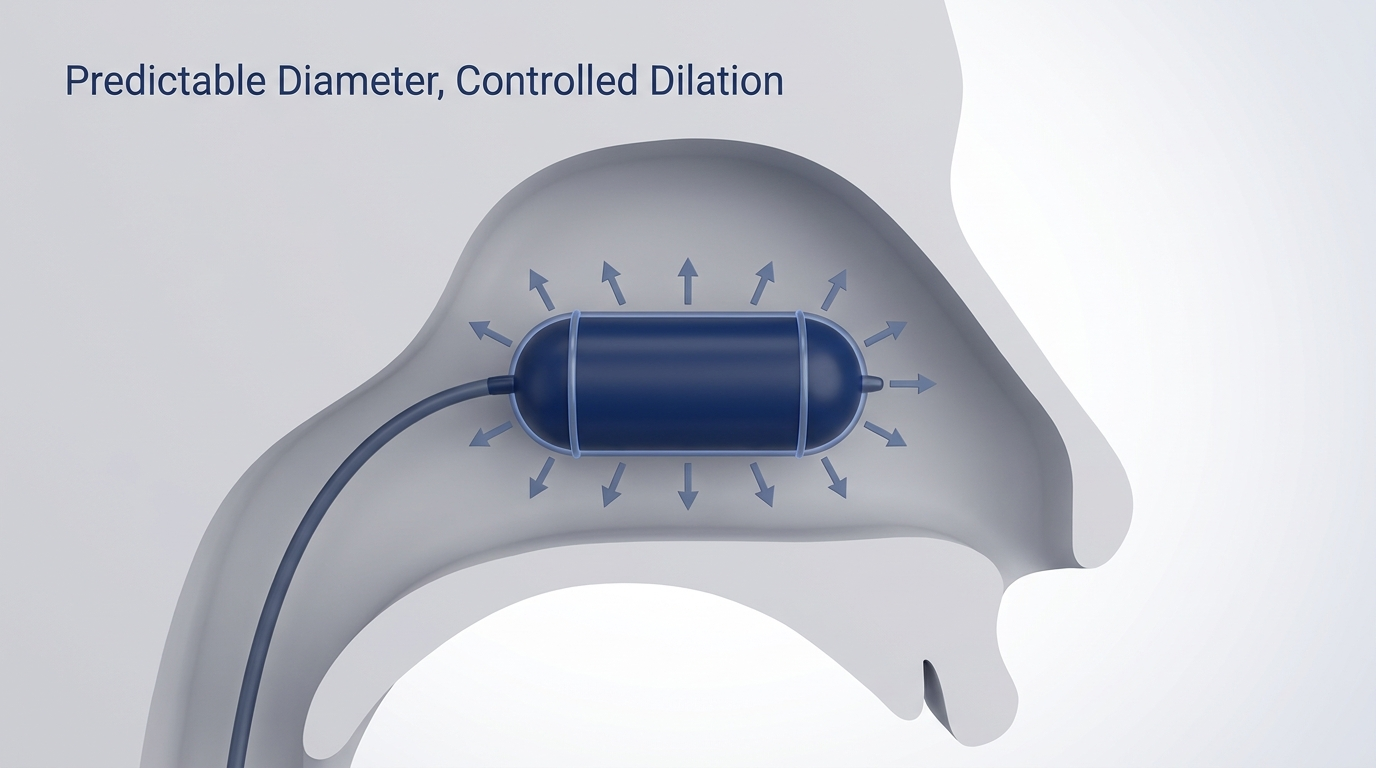
In nasal surgery, one goal of minimally invasive approaches is to reduce disruption of the nasal lining—specifically, to reduce or avoid mucoperichondrial flap elevation when appropriate. The ClearPath Nasal Balloon (CNB) is a device used in a balloon-assisted septoplasty technique designed to mobilize bony septal deviations while aiming to reduce or avoid mucoperichondrial flap elevation, packing, and prolonged anesthesia compared with some traditional septoplasty approaches. For a side-by-side overview, see ClearPath vs traditional septoplasty—recovery, safety, and results compared.
What outcomes have been reported (early evidence)
Early retrospective evidence with CNB has reported:
• Safety: In 107 consecutive CNB cases, no major complications (septal perforation, hematoma, synechia, or conversion to traditional flap-based surgery).
• Imaging: In 23 patients with pre/post CT scans, mean alignment improved 45% at maximal deviation and 22% at the nasolacrimal duct (p=0.005).
• Symptoms: In 43 patients with one-month questionnaires, SNOT-22 improved from 58.7 to 44.8 (a 23.8% reduction, p=0.02).
[Dillard 2026; publication timing/status should be verified.]
Balanced takeaway
These findings are promising, but the dataset is retrospective with a modest CT subgroup. Larger prospective studies are needed to clarify who benefits most and how outcomes compare across longer follow-up windows. [Dillard 2026]
Early evidence suggests some patients may trade less flap disruption for a calmer initial recovery, but careful selection and more data are essential.
Who might benefit most from less flap disruption—and who may not
Situations where less dissection may be advantageous (general principles)
Less tissue lifting may be attractive for patients who prioritize:
• faster early comfort
• less soft-tissue disruption
• selected deviations where extensive exposure isn’t necessary
This is part of the rationale behind minimally invasive septoplasty approaches that try to preserve more lining tissue when clinically appropriate. [Dillard 2026]
When traditional flap dissection may still be necessary
A surgeon may recommend traditional flap dissection for:
• complex or severe deviations
• revision surgery
• combined procedures requiring broader access
• situations where visibility is essential for safety and precision
[Jain 2024]
The “best” approach is the one that safely meets your goals for your specific anatomy—not the least or most invasive option by default.
Patient FAQs (high-clarity)
Does more invasive always mean better correction?
Not always. More exposure can help in complex cases, but it can also increase early inflammation. The goal is to match your anatomy and surgical target with an acceptable recovery profile.
Why does flap elevation increase swelling?
Flap elevation separates tissue planes, stretches small vessels, and increases local inflammatory signaling. That combination can lead to more fluid accumulation and tenderness in the early healing period. [StatPearls, 2024]
How long does tissue take to fully heal?
Many people feel meaningfully better within days to weeks, but remodeling can continue for weeks to months depending on the site and procedure. Planning ahead for pain and swelling is important. [CDA, 2013]
What questions should I ask my surgeon about flap vs flapless options?
• How much traditional flap dissection (if any) is expected in my case?
• Is flap elevation required for my anatomy or goals?
• What should I expect for postoperative swelling and pain in the first week?
• Will I need packing, and for how long?
• What are my bleeding risks and how are they minimized?
• What is the backup plan if visibility/access is limited?
If you’re exploring balloon-assisted approaches, this walkthrough may help: what to expect during an office-based balloon septoplasty.
Arrive with clear goals and questions so you and your surgeon can align the surgical plan with your recovery preferences.
Conclusion: the tradeoff—access and visibility vs tissue preservation
• Traditional flap dissection can be traumatic because it combines incision, flap elevation, retraction, and suturing—often with temporary blood-supply disruption as a key biological stressor.
• That trauma may show up as postoperative swelling and pain, bleeding/oozing, or occasional wound-healing issues, especially in the early phase.
• Minimally invasive or flap-sparing approaches (including techniques that aim to reduce mucoperichondrial flap disruption in selected nasal cases) may reduce early soft-tissue trauma—but they aren’t right for every situation, and long-term outcomes vary by indication and anatomy.
Work with your ENT to choose the approach that best balances precision, safety, and recovery for your anatomy and goals.
References
Cho et al. “Dimensional change of the healed periosteum on surgically created defects” (2011). https://pmc.ncbi.nlm.nih.gov/articles/PMC3175497/
StatPearls. “Oral Flap Design” (2024). https://www.ncbi.nlm.nih.gov/books/NBK610687/
Jain et al. “Comparative efficacy of flapped versus flapless dental implant procedures: A meta-analysis” (2024). https://pmc.ncbi.nlm.nih.gov/articles/PMC11226941/
Gu et al. “Incidence and risk factors of postoperative complications following periodontal flap surgery” (2025). https://pmc.ncbi.nlm.nih.gov/articles/PMC12086267/ and/or https://www.frontiersin.org/journals/dental-medicine/articles/10.3389/fdmed.2025.1668844/full
Canadian Dental Association. “Managing Postoperative Pain Following Periodontal Surgery” (2013). https://jcda.ca/article/d66
Dillard et al. Rhinology Online (2026) 9:18–23. doi:10.4193/RHINOL/25.018
This article is for educational purposes only and is not medical advice. Please consult a qualified healthcare provider for diagnosis and treatment.

Dr. David G. Dillard
Author
Share it with others!