Why Sutureless Surgery Is the Future of Recovery
“Sutureless” doesn’t mean “no surgery.” It means surgery that reduces or avoids stitches when appropriate—often by using smarter techniques, specialized devices, and newer biomaterials that help tissues seal or stay in place without traditional thread.
For patients, the appeal is easy to understand: in selected situations, minimally invasive approaches may be associated with reduced surgical trauma, less scarring, and a faster recovery. At the same time, not every procedure can be done without sutures, and not every person is a candidate for a suture-sparing approach.
Below is a plain-English guide to what sutureless surgery is, why it’s gaining momentum, where it’s already showing measurable results (including a clear ENT example), and what still needs to happen before it becomes routine in more operating rooms.
What “Sutureless” Surgery Means—In Plain English
Sutures vs sutureless approaches
Traditional sutures are medical “thread” used to close tissue or secure structures. They work well, but they can add steps, time, and tissue handling to a procedure.
A helpful analogy: if sutures are like sewing fabric together, suture-sparing methods aim to act more like precision fasteners or sealants—still secure, but sometimes faster and with less “poking and pulling” of delicate tissue. That doesn’t make sutures outdated; it just expands the toolkit.
Sutureless surgery describes techniques that reduce the need for stitches by relying on one (or more) of the following instead:
- Device-enabled tissue repositioning (moving tissue into a better position without extensive cutting or sewing)
- Biomaterials that help tissues bond, seal, or fixate in specific settings
- Surgical sealants that support closure or reduce leakage/bleeding risk in carefully selected uses
Importantly, “sutureless” often means fewer sutures—not necessarily zero. And the goal is not convenience. The goal is to support healing while minimizing unnecessary tissue disruption.
Not “no tools,” just different tools
A suture-sparing approach is not “doing less” in a careless way. It’s doing things more precisely, with tools designed to limit dissection and simplify closure when evidence supports it. For a plain-language overview of where minimally invasive septoplasty fits relative to traditional approaches, see minimally invasive vs. traditional septoplasty (https://www.clearpathnasal.com/blog/minimally-invasive-vs-invasive-where-clearpath-fits).
This shift is happening now because the field has progressed beyond theory into real product development and clinical-stage applications of tissue-joining biomaterials. Some examples appear on manufacturer pages describing polymer-based platforms and clinical programs (see Tissium Pipeline, accessed 2026: https://tissium.com/products/pipeline).
Why fewer stitches can matter (sometimes)
Even when sutures are placed perfectly, they can still be associated with trade-offs—more tissue passes, more knots, and more handling. In certain procedures, reducing those steps may mean less swelling, fewer “foreign-body” surfaces, and a simpler post-op course. The key word is may: anatomy, technique, and healing biology still drive outcomes.
– In short: sutureless means fewer stitches where it’s safe and useful, not a promise of zero sutures. –

Why Sutureless Surgery Is Gaining Momentum Now
Biomaterials that bond or seal tissue
Modern biomaterials can be engineered to interact with tissue in specific ways—such as forming a seal, supporting fixation, or acting as a barrier while healing occurs. In patient terms, these materials aim to replace some jobs that stitches used to do, but only in the right clinical scenario. Manufacturer pipelines now describe commercial products and clinical testing across indications—for example, atraumatic peripheral-nerve reconstruction programs and additional efforts in hernia fixation and cardiovascular sealing (company source: Tissium Pipeline, accessed 2026: https://tissium.com/products/pipeline). These pages are not independent clinical proof, but they signal active development.

3D printing and custom-fit implants
3D printing enables custom-fit components that can help surgeons reconstruct anatomy with less trimming, pulling, or tension. While 3D printing doesn’t automatically mean “no sutures,” it supports the broader movement toward precision and atraumatic (tissue-sparing) repair.
Device-enabled, tissue-sparing techniques (including ENT)
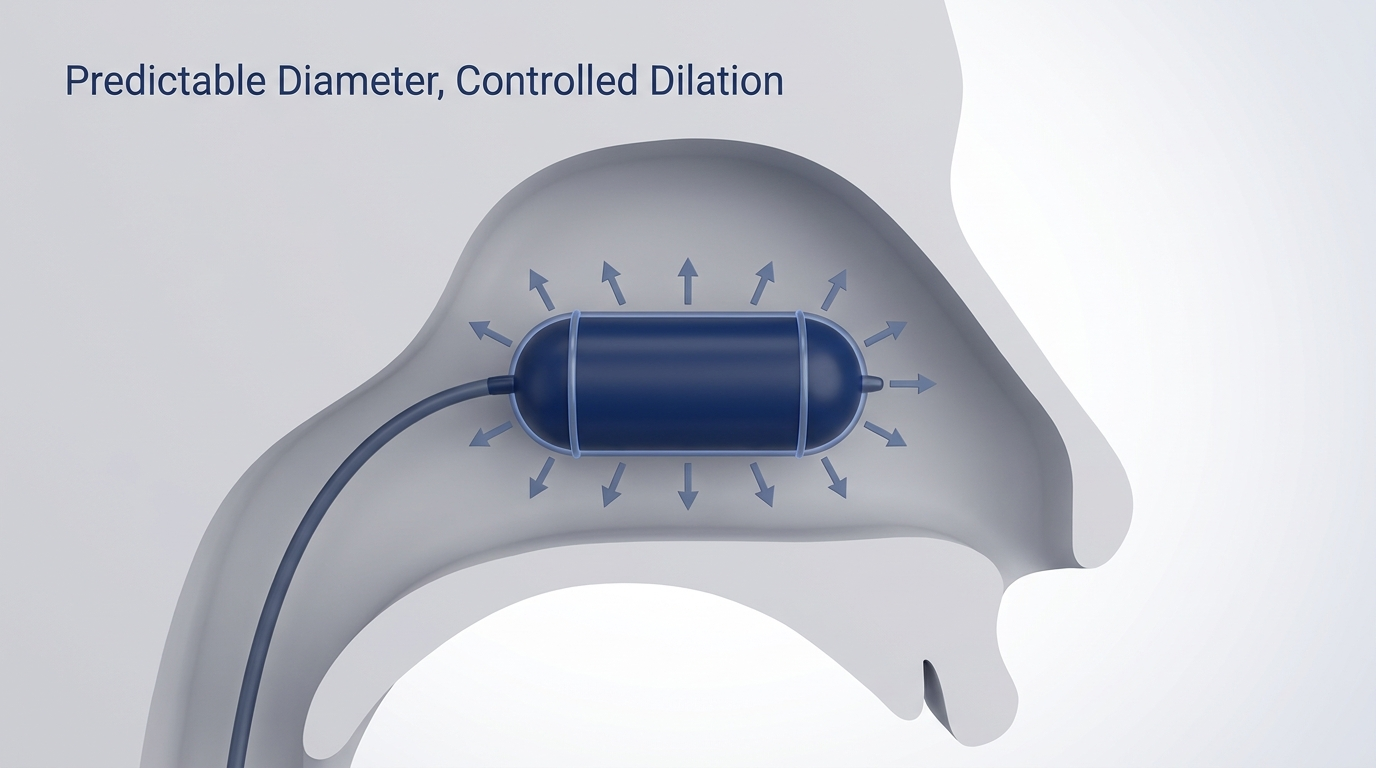
Device-enabled techniques can reduce cutting and dissection in the first place. In ENT, a clear example is balloon-assisted septoplasty, which uses a device-based approach aimed at repositioning septal deviations with less disruption than traditional methods in selected patients. For a quick primer, see what balloon-assisted septoplasty is (https://www.clearpathnasal.com/blog/what-is-balloon-assisted-septoplasty).
– Bottom line: technology is making precise, tissue-sparing repair more practical across more procedures. –

The Patient Benefits Driving the Shift (When You’re a Good Candidate)
Less cutting and tissue disruption
In general, less cutting and less tissue elevation can matter because it may reduce:
- swelling
- bleeding
- post-op discomfort
That’s the logic behind many minimally invasive techniques: do what’s needed, but avoid “extra” trauma that doesn’t add value. For context specific to nasal surgery, here’s where minimally invasive septoplasty fits (https://www.clearpathnasal.com/blog/minimally-invasive-vs-invasive-where-clearpath-fits).
Potential for simpler recovery and fewer “extras”
Some suture-sparing approaches aim to reduce add-ons that patients often worry about—like nasal packing after septoplasty or longer time under anesthesia. This doesn’t mean those steps disappear in every case, but the design goal is often an easier post-op course for appropriate candidates. For patient-oriented details, see recovery and safety compared with traditional septoplasty (https://www.clearpathnasal.com/blog/clearpath-vs-traditional-septoplasty-recovery-safety-results).
Cosmetic benefits can be a side effect
“Cosmetic” isn’t always the primary goal, but less scarring can be a side benefit—especially in procedures where external stitches would otherwise be visible. Even when surgery is internal (as with many nasal procedures), reducing tissue trauma may help limit swelling and tenderness during healing.
– Key idea: patients care about outcomes; tissue-sparing methods aim to get there with less disruption when it’s appropriate. –

Real-World Examples: Sutureless Surgery Is Moving Beyond “Experimental”
Across healthcare, tissue-joining biomaterials and sealing approaches have moved into real development pipelines and clinical evaluation. Company product pages and early clinical reports indicate practical engineering and medical focus, though they are not, by themselves, definitive proof that a given method is superior (Tissium Pipeline, accessed 2026: https://tissium.com/products/pipeline).
ENT example: balloon-assisted septoplasty as a tissue-sparing, low-suture direction
One of the most patient-relevant ENT examples is balloon-assisted septoplasty, part of the broader “less cutting, less disruption” movement. For a simple explainer, see balloon-assisted septoplasty (https://www.clearpathnasal.com/blog/what-is-balloon-assisted-septoplasty).
ClearPath is a device used in a force-directed balloon-assisted endoscopic septoplasty technique described by the manufacturer and in a published outcomes series (manufacturer source: https://clearpathnasal.com/for-physicians; Dillard et al., 2026: http://rhinologyonline.org/Rhinology_online_issues/manuscript_2530.pdf). It is best understood as suture-sparing and tissue-sparing—not a promise that stitches can never be used, but a design philosophy that aims to reduce unnecessary dissection and recovery burdens where feasible.
– Takeaway: real devices and early studies exist, but procedure- and patient-specific evidence should drive decisions. –
What the Early Clinical Evidence Shows (A Clear Example From Septoplasty)
Safety signals (large consecutive series)
In a series of 107 consecutive force-directed balloon-assisted endoscopic septoplasty procedures, the authors reported no major complications, including no septal perforation, hematoma, synechiae, or conversion to traditional flap-based surgery (Dillard et al., 2026). This is encouraging but represents findings from a single series; larger comparative studies and longer follow-up are needed.
Imaging results (alignment improvement on CT in a subset)
Among 23 patients with pre- and post-operative CT scans:
- mean alignment improved 45% at the point of maximal deviation
- and 22% at the nasolacrimal duct
- with both results reported as statistically significant (p = 0.005)
The authors also noted that 78% achieved at least 30% improvement, and none worsened in that CT subset (Dillard et al., 2026).
How patients felt (symptom improvement)
In 43 patients who completed a symptom questionnaire (SNOT-22) at one month, average scores improved from 58.7 to 44.8—a 23.8% reduction (p = 0.02), with the biggest gains reported in congestion, headache/facial pressure, and sleep quality (Dillard et al., 2026). This is early, short-term symptom data.
Scale: why small improvements matter
Because septoplasty is so common, even incremental improvements—less packing, less tissue disruption, shorter anesthesia time for some cases, fewer post-op visits for complications—could meaningfully affect patient experience overall. For practical considerations, see recovery and safety compared with traditional septoplasty (https://www.clearpathnasal.com/blog/clearpath-vs-traditional-septoplasty-recovery-safety-results).
– Summary: early results look promising for selected patients, but broader, longer-term studies are essential to define where these techniques truly excel. –
What Still Needs to Happen Before Sutureless Surgery Becomes “Standard”
Adoption will be procedure-by-procedure (not one-size-fits-all)
Whether a suture-sparing method becomes standard depends on:
- procedure-specific clinical trials (ideally comparative)
- long-term outcomes (durability of results)
- revision rates
- standardized technique and aftercare protocols
The protocol challenge: packing and splinting aren’t standardized
Septoplasty aftercare highlights why standardization matters. A systematic review found no established consensus on post-op packing and splinting practices in septoplasty/rhinoseptoplasty literature (https://pmc.ncbi.nlm.nih.gov/articles/PMC10118399/). When aftercare varies widely, it becomes harder to compare techniques fairly and to identify what truly improves recovery.
Why long-term follow-up matters
Patients care about durable outcomes: sustained breathing improvement, risk of revision, and late complications. Early outcomes can be encouraging, but longer follow-up and broader studies help determine which sutureless approaches belong in mainstream care.
– Expect careful, stepwise adoption: evidence first, then wider use where benefits are proven. –
Who Might Benefit Most From Suture-Sparing Approaches?
Patients prioritizing faster recovery and less tissue disruption
If your top priorities are returning to work faster, minimizing swelling, or avoiding a more extensive recovery, it’s reasonable to ask whether a suture-sparing or tissue-sparing approach exists for your condition.
Situations where avoiding extensive dissection may help
When a technique can achieve the goal (repair, repositioning, sealing) with less tissue elevation or cutting, it may reduce post-op discomfort for some patients. This is not guaranteed—but it’s part of why these methods are being developed.
ENT example: nasal obstruction from septal deviation
If you’re considering septoplasty for nasal obstruction, eligibility for balloon-assisted approaches depends on anatomy, deviation type, and clinician assessment. For a practical overview, see who is a good candidate (https://www.clearpathnasal.com/blog/best-candidates-for-balloon-septoplasty-with-clearpath).
– The “best” option depends on your anatomy, goals, and the procedure’s evidence—ask your surgeon to tailor the plan. –
Questions to Ask Your Surgeon
- Is a suture-sparing option appropriate for my specific anatomy?
- What evidence exists for this technique in this exact procedure?
- What is the recovery plan—will I need packing, splints, or stitches?
- What are the short- and long-term risks, including the chance of revision?
For background as you compare techniques, this overview of minimally invasive vs. traditional septoplasty may help (https://www.clearpathnasal.com/blog/minimally-invasive-vs-invasive-where-clearpath-fits).
– Good questions lead to clearer expectations and better-aligned decisions. –

FAQ
Is sutureless surgery safe?
Safety depends on the procedure and the technique. In the septoplasty example above, a series of 107 consecutive balloon-assisted endoscopic septoplasty procedures reported no major complications in that cohort (Dillard et al., 2026). Still, broader evidence and long-term data are important before any approach becomes a default.
Does “sutureless” mean no incisions?
Not necessarily. “Sutureless” refers to reducing the need for stitches, not avoiding all incisions. Some procedures still require incisions, but may use fewer sutures—or different closure/support methods—depending on the case.
Will recovery be faster without stitches?
Sometimes, but not always. Recovery depends on how much tissue was disrupted, how your body heals, and what aftercare is needed (like packing or splints). For context specific to septoplasty, see recovery and safety compared with traditional septoplasty (https://www.clearpathnasal.com/blog/clearpath-vs-traditional-septoplasty-recovery-safety-results).
Is balloon-assisted septoplasty “sutureless”?
It’s better described as suture-sparing/tissue-sparing rather than “never uses sutures.” Balloon-assisted septoplasty (including procedures performed with the ClearPath device) is part of the broader movement toward minimizing dissection and improving recovery experience where appropriate (manufacturer source: https://clearpathnasal.com/for-physicians; Dillard et al., 2026).
– The safest answers about candidacy, risks, and recovery come from your treating clinician. –
Conclusion—Less Trauma, More Precision (With Evidence)
Sutureless surgery is best understood as a direction: less unnecessary cutting, fewer stitches when safe, and smarter tools that support healing. The momentum is real—driven by advances in biomaterials, surgical sealants, 3D printing, and device-enabled techniques that aim to reduce surgical trauma. At the same time, the path to “standard of care” will be careful and procedure-specific—built on comparative trials, standardized protocols, and long-term outcomes.
If you’re considering septoplasty (or you’ve been told you might need it), ask your local ENT whether a minimally invasive, tissue-sparing, possibly suture-sparing technique—including device-assisted options like balloon septoplasty—could fit your anatomy and goals, and what the evidence-based trade-offs are in your specific case.
– Progress here is meaningful when it’s measurable, durable, and matched to the right patient. –
Medical disclaimer
This article is for educational purposes only and is not medical advice. Please consult a qualified healthcare provider for diagnosis and treatment. Your individual situation is unique; only a clinician who has examined you can recommend what’s appropriate for you.
References
- Tissium. Pipeline / Products (manufacturer source; accessed 2026). https://tissium.com/products/pipeline
- ClearPath Nasal. For Physicians / Clinical Evidence (manufacturer source; accessed 2026). http://clearpathnasal.com/for-physicians
- Dillard J, et al. Outcomes of force-directed balloon-assisted endoscopic septoplasty. Rhinology Online. 2026;9:18–23. http://rhinologyonline.org/Rhinology_online_issues/manuscript_2530.pdf
- Intranasal packing and splinting following septoplasty and rhinoseptoplasty (systematic review). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC10118399/

Dr. David G. Dillard
Author
Share it with others!