Why “Submucous Resection” Is Less Common Today (And When It Still Makes Sense)
If you’ve been told you might need surgery for a deviated septum, you may see older terms in your paperwork—especially submucous resection, often shortened to SMR. While SMR played an important role in the history of nasal surgery, many ENTs now prefer newer approaches that aim to fix breathing with less tissue removal and better long-term support. That doesn’t mean SMR is never appropriate—it means it’s no longer the default for many routine cases.
Below is a patient-friendly explanation of what SMR is, why it’s used less often today, what “modern septoplasty” does differently, and why a careful evaluation of the whole nasal airway matters.
What Is a Submucous Resection (SMR)?
The traditional goal: “remove the blockage”
Your nasal septum is the wall that divides the inside of your nose into left and right sides. If it’s deviated (bent), airflow can be reduced—sometimes enough to cause chronic congestion, mouth breathing, sleep disruption, and exercise intolerance. For a quick primer, see deviated septum explained: https://www.clearpathnasal.com/blog/deviated-septum-explained-symptoms-causes-and-modern-treatment-options
A submucous resection is a classic surgical technique designed to straighten the airway by lifting the lining (mucosa) and removing larger portions of the underlying septal cartilage and/or bone beneath that lining. Historically, the main idea was straightforward: remove the part that’s blocking airflow.¹
A helpful way to picture this: SMR treats the septum a bit like a “bent divider” that you can simply cut back to open space. That can work in select cases—but it doesn’t fully reflect the septum’s role as a support structure.
Why SMR became popular historically
SMR became widely used in an era when surgeons had fewer visualization tools (like today’s endoscopes) and fewer reconstruction options. In that setting, removing the deviated segment was often the most direct way to open the airway.¹²
SMR is still performed in selected situations, but it’s less commonly used as the default approach today because modern techniques can often correct the problem while preserving more of the septum’s support.¹³⁴
In short: SMR opened airways by removing bent tissue; modern surgery more often aims to correct the bend while preserving support.

The Main Reason SMR Is Falling Out of Favor: It Can Remove More Tissue Than Necessary
Modern septoplasty is tissue-sparing by design
When people compare SMR vs septoplasty, the big difference is how much septal tissue is removed—and what’s done to maintain strength and shape afterward. SMR often involves broader resection of cartilage or bone to “take out the bend.” Modern septoplasty typically focuses on targeted correction—removing only what’s necessary, while preserving, reshaping, or repositioning key support tissue.³⁴
This tissue-sparing mindset is one reason many surgeons now view submucous resection as an older approach for many routine cases of deviated septum surgery.³⁴
Why “less removal” can be better for breathing and stability
It’s easy to think of a deviated septum as “extra stuff in the way.” But the septum isn’t just a divider—it’s part of the nose’s internal framework. If too much is removed, the nose can lose structural stability, which can affect both function (breathing) and appearance.³⁵
Modern approaches generally aim to improve airflow without over-removing cartilage, preserve the lining (to reduce scarring risks), and protect the most important support areas.
Bottom line: The goal isn’t to remove the septum—it’s to reshape and stabilize it so it supports good airflow long-term.

SMR Can Weaken Structural Support (And That Can Change the Outside of the Nose)
The importance of preserving the “L-strut” (dorsal + caudal support)
Surgeons often describe a key structural support region called the L-strut—think of it as the nose’s internal support beams: the dorsal portion helps support the bridge, and the caudal portion helps support the tip area. In modern septoplasty, preserving this framework (or reconstructing it when necessary) is emphasized because it helps maintain both stability and airflow.³⁴
A practical analogy: if the septum is the “central support stud” inside a wall, you can’t simply remove a large section without risking sagging or shape changes elsewhere. Modern septoplasty tries to straighten the stud while keeping it load-bearing.
What can happen when too much support is removed
When too much septal support is removed—especially if the L-strut isn’t adequately preserved—structural changes can occur. Patient-facing examples often discussed in surgical literature include drooping nasal tip, columellar retraction, supratip depression, and saddle-nose deformity.¹³ Not everyone will experience these issues, and surgical technique matters, but the possibility helps explain why a more conservative, support-preserving approach has become the norm for many ENTs.³⁴
Why anterior deviations are a problem for older “resection-heavy” strategies
Not all deviations are equal. Bends closer to the front of the septum (anterior deviations) can be more structurally important and more visible. Historically, more aggressive resection in these areas carried greater risk of altering support.¹ Today, modern endoscopic and reconstructive techniques can allow better visualization and more precise correction—one more reason older, resection-heavy strategies are less favored for many anterior problems.¹³⁴
Takeaway: Preserving (or rebuilding) the L-strut helps keep both breathing and appearance stable over time.

A Deviated Septum Is Not the Only Cause of Nasal Obstruction
The “missed diagnosis” problem: nasal valve obstruction
Even a well-performed septoplasty may not fully solve congestion if the real bottleneck is elsewhere. One major example is nasal valve obstruction—the nasal valve is the narrowest part of the nasal airway and a common, under-recognized cause of blockage. Septoplasty failure rates have been reported around 19%–50% when nasal valve obstruction is missed.³⁴ These figures vary by study, how “failure” is defined, and whether other factors (like turbinates or rhinitis) were addressed—so they’re best understood as a reminder to evaluate the whole airway, not a fixed prediction for any one patient. To learn more, see why the nasal valve matters for breathing: https://www.clearpathnasal.com/blog/understanding-the-nasal-valve-why-it-matters-for-breathing
Other common contributors that SMR alone won’t fix
Even when a deviated septum is present, other issues can contribute to symptoms, including turbinate hypertrophy (enlarged turbinates that take up space), rhinitis (allergic or non-allergic inflammation), synechiae (adhesions or scar tissue), and residual deviation (the most important area wasn’t fully corrected).³⁵ For a deeper dive into turbinate enlargement, see: https://www.clearpathnasal.com/blog/understanding-turbinate-hypertrophy

What modern evaluation looks like
A more complete airway evaluation may include nasal endoscopy (a small camera to see internal structures clearly), a targeted exam for valve collapse or narrowing, and identifying turbinate hypertrophy and inflammatory disease.³⁵ This kind of workup helps tailor treatment so the plan fits your anatomy—not just a one-size-fits-all operation.
In essence: Lasting relief comes from matching treatment to all the causes of blockage, not just the septum.
What Replaces SMR Today? Conservative Septoplasty + Reconstruction When Needed
The modern goals
In many practices, modern septoplasty focuses on correcting the specific deviation that limits airflow most, preserving mucosa (the lining) when possible, and preserving the dorsal-caudal L-strut while reconstructing support if it’s compromised.³⁴ The goal isn’t to do “less surgery” at all costs—it’s to do the right amount of surgery in the right location to improve breathing while keeping the nose stable.
Better tools and visualization (endoscopic septoplasty)
Endoscopic approaches can help surgeons see and address precise problem areas, especially deeper or more complex deviations. This can reduce blind removal and support a more targeted plan—often a key difference in the SMR vs septoplasty conversation today.³⁴ For a deeper comparison, you can read: https://www.clearpathnasal.com/blog/endoscopic-septoplasty-vs-open-surgery-which-is-better
Short version: Today’s septoplasty seeks precision—fix the area that matters most and preserve the supports that matter most.

Minimally Invasive Septal Techniques Are Shifting Expectations (Selected Data)
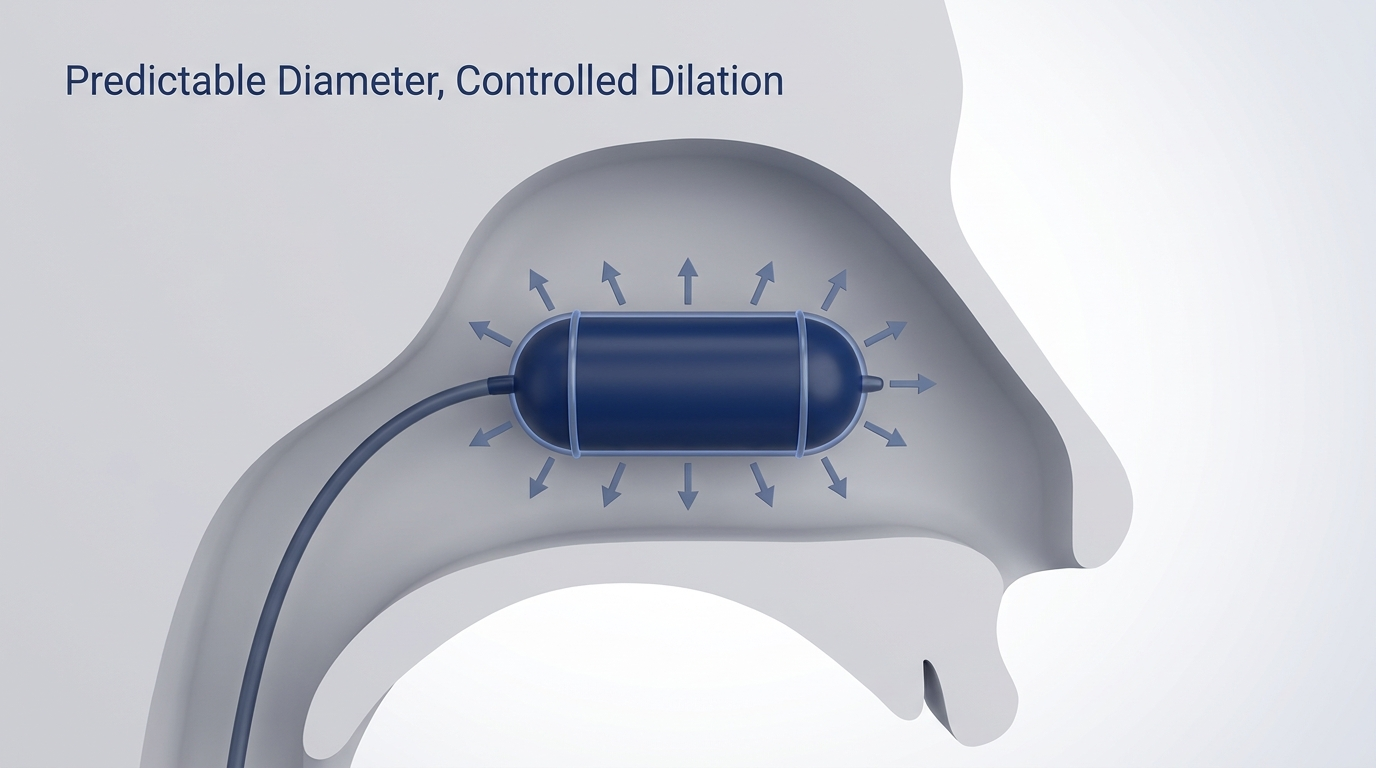
Promising new approaches aim to correct certain septal deviations with less dissection. One example is balloon-assisted septoplasty, including use of the ClearPath device (a balloon-based system designed to help mobilize septal deviations under endoscopic visualization). If you’re new to the concept, start here: https://www.clearpathnasal.com/blog/what-is-balloon-assisted-septoplasty
The design intent: mobilize deviations while limiting flap elevation
Balloon-assisted approaches are designed to mobilize deviations while reducing or avoiding extensive elevation of the mucoperichondrial flap. Potential benefits may include less packing and shorter anesthesia time compared with traditional, flap-based techniques in selected cases.⁶
Safety snapshot from a consecutive-case series
In a retrospective series of 107 consecutive cases, investigators reported no major complications—specifically no septal perforation, hematoma, synechiae, or conversion to traditional flap-based surgery.⁶
What imaging and symptom surveys showed (early outcomes)
CT subgroup (n = 23): mean alignment improved 45% at the point of maximal deviation and 22% at the nasolacrimal duct (p = 0.005).⁶
Symptom improvement (n = 43 at 1 month): SNOT-22 mean improved from 58.7 to 44.8 (a 23.8% reduction; p = 0.02), with notable improvements in congestion, headache or facial pressure, and sleep.⁶
These were retrospective, early data with modest subgroups, and larger prospective studies are still needed.⁶ To compare options, see: https://www.clearpathnasal.com/blog/clearpath-vs-traditional-septoplasty-recovery-safety-results
Take-home: Minimally invasive options are emerging, but decisions should still be individualized and evidence-informed.
Is SMR Ever Still Appropriate?
“Outdated” doesn’t mean “never”
Calling submucous resection “outdated” doesn’t mean it has no role. SMR has historical data showing acceptable satisfaction and complication rates, and it may still be considered in selected circumstances.² The bigger shift is that many surgeons now prefer techniques that preserve support whenever possible—especially when modern visualization and reconstruction options are available.³⁴
How to talk with your ENT about the right approach for you
If you’re considering deviated septum surgery, ask whether nasal valve obstruction is being evaluated, whether the L-strut will be preserved, whether turbinate hypertrophy will be treated if needed, which technique is recommended for your deviation location (front vs back), and whether you are a candidate for a minimally invasive option such as balloon-assisted septoplasty (including ClearPath where available).³⁴⁵
Bottom line: The “right” operation depends on your anatomy, your symptoms, and your goals—discuss options and trade-offs with a board-certified ENT.
Key Takeaways (Patient-Friendly Summary)
SMR is used less often as a default because it can remove more tissue than needed and may weaken nasal support structures.³⁴
Modern septoplasty focuses on targeted correction, mucosal preservation, and protecting or rebuilding key support.³⁴
Persistent obstruction often involves more than the septum—especially nasal valve problems and turbinate hypertrophy.³⁴⁵
Minimally invasive septoplasty, including balloon-assisted septoplasty with the ClearPath device, is being studied with early safety and outcome signals reported in recent series.⁶
References
1. Archives of Medicine and Health Sciences (2018). “Evolution of Correction of the Deviated Nasal Septum – A Historical Overview.” https://journals.lww.com/armh/fulltext/2018/06020/evolution_of_correction_of_the_deviated_nasal.22.aspx
2. Low WK, Willatt DJ. (1992). “Submucous resection for deviated nasal septum: a critical appraisal.” https://pubmed.ncbi.nlm.nih.gov/1488674/
3. StatPearls/NCBI Bookshelf. (2022). “Septoplasty.” https://www.ncbi.nlm.nih.gov/books/NBK567718/
4. Medscape. (2025). “Septoplasty Treatment & Management.” https://emedicine.medscape.com/article/877677-treatment
5. American Academy of Otolaryngology–Head and Neck Surgery. (2014). “Clinical Indicators: Septoplasty.” https://www.entnet.org/resource/clinical-indicators-septoplasty
6. Dillard et al. Rhinology Online (2026);9:18–23. doi:10.4193/RHINOL/25.018
Call to action
If you’re weighing septum surgery, bring your symptoms and goals to a board-certified ENT and ask for a full airway evaluation (septum plus valves and turbinates). If you’re curious about newer options, ask your local ENT whether you might be a candidate for balloon-assisted septoplasty and whether ClearPath is an available alternative in your area.
Medical disclaimer
This article is for general educational purposes only and does not provide medical advice. Diagnosis and treatment decisions should be made with a qualified clinician who can evaluate your specific anatomy, symptoms, and medical history. Please consult a qualified healthcare provider for diagnosis and treatment.

Dr. David G. Dillard
Author
Share it with others!