Why ClearPath Is “Force-Directed” (and What That Really Means Compared With Other Nasal Balloons)
If you’ve been researching newer options for deviated septum treatment, you may have seen ClearPath described as a “force-directed” system. That phrase can sound technical—but the basic concept is simple: it’s a device intended to aim pressure toward a specific part of the septum, rather than letting pressure spread evenly in every direction.
Below is a patient-friendly explanation of what a “force-directed” nasal balloon is meant to do, how ClearPath works (as a device), what early published outcomes show, and what’s still unknown. [1–4]
Quick Take: What “Force-Directed” Means in Plain Language
The simple idea
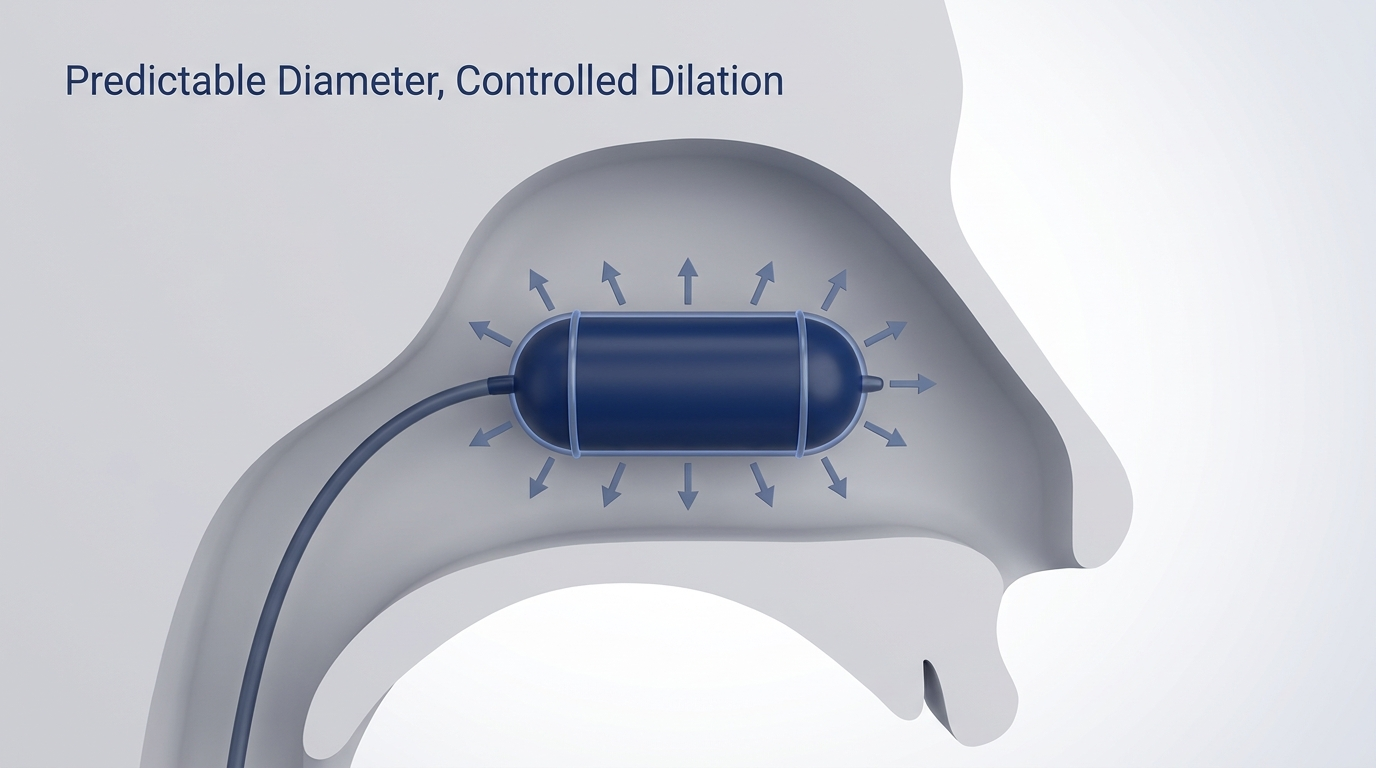
A standard balloon expands outward in all directions when it’s inflated. ClearPath is described as “force-directed” because it pairs an inflatable balloon with a shaped guide (often called a spatula). Together, the design is intended to aim pressure toward a chosen spot on the septum instead of pushing broadly across nearby areas. [1,2]
In other words, a “force-directed” nasal balloon is about where the pressure is intended to go—not just the fact that a balloon inflates.
A concrete analogy (why “direction” matters)
Think of trying to straighten a slightly bent cabinet door. If you press broadly on the whole door, you might stress the hinges and frame. If you push at the right point—closer to where the door is misaligned—you’re more likely to get the correction you want with less spillover force. That’s the logic behind directional force: focus the push where the deviation seems most relevant, instead of pressurizing everything equally. This is a design rationale, not proof of better symptom, airflow, or safety outcomes. [2,3]
Why this matters for patients
The patient-centered goal of directional force is to reposition a deviation while limiting unnecessary pressure on nearby structures (for example, the nasal sidewall or turbinates) and, in selected cases, to limit dissection compared with some traditional approaches. These are design and technique intentions; they are not guarantees of clinical superiority. [1–3]
Summary: Directional force is a device design idea about where pressure is focused, not a promise of better results.

A 60-Second Refresher: What Happens in a Deviated Septum
What the septum is
The nasal septum is the wall inside your nose that separates the left and right nasal passages. It includes cartilage and bone, and those tissues can deviate in different ways.
How deviation can block airflow
When the septum bends or shifts to one side, it can narrow a nasal passage and contribute to symptoms such as congestion, reduced airflow, facial pressure, or sleep disruption. Symptoms vary widely from person to person.
Why “where” the bend is matters
Not all deviations are the same; the location and pattern can matter to both symptoms and procedural planning. In ClearPath-related literature, you’ll see discussion of targeting the “point of maximal deviation”—the area where the septum is most off-center. [3] For more on that concept, see point of maximal deviation: https://www.clearpathnasal.com/blog/how-clearpath-addresses-point-of-maximal-deviation
Summary: Where a deviation occurs matters for planning, which is why targeting a specific spot comes up in these device discussions.

What Makes ClearPath “Force-Directed”: The Balloon + Spatula Design
The two-part mechanism
ClearPath’s design is commonly described as two parts working together. [1,2]
Balloon: When inflated, the balloon creates inflation pressure.
Spatula or guide: The shaped guide is intended to redistribute and direct that pressure toward the intended septal segment and help limit pressure on surrounding anatomy.
This combination is what manufacturer and author materials refer to when they describe ClearPath as a “force-directed” nasal balloon system. A practical walkthrough of the steps is available here: how the ClearPath Nasal Balloon works (step-by-step) https://www.clearpathnasal.com/blog/how-the-clearpath-nasal-balloon-works-a-step-by-step-guide
The intended benefit: controlled pressure where it’s needed
Applying force to change alignment can be more effective when it’s applied at the right point—similar to how pushing a door is easiest at the handle rather than randomly across the surface. The device concept is that directional force may help focus the mechanical effect where the deviation is most significant (for example, the point of maximal deviation), rather than applying equal pressure across the whole area. [1–3]
What “force-directed” does not automatically mean
“Force-directed” describes a mechanical strategy; it does not ensure better outcomes for every patient or every deviation pattern. The device does not “know” where to go on its own; its geometry and orientation are meant to channel force, but anatomy is variable. Whether this strategy fits a specific deviation pattern is a clinical judgment. [3]
Summary: The balloon-and-spatula design aims pressure, but fit and outcomes depend on anatomy and clinical technique.
Are Other Nasal Balloons Really “Not Directional”? A Careful, Evidence-Based Answer
What manufacturer comparisons claim
Manufacturer materials describe many balloon-only designs as expanding more radially (outward in all directions), while ClearPath is described as aiming force toward the side the system is oriented toward. [1]
The key nuance
“Radial vs directional” is a useful engineering concept, but the medical literature does not establish a universal, head-to-head clinical finding that every other balloon behaves the same way in real patients across all anatomies. It is more precise to say the following. [2]
ClearPath is specifically designed and described as a “force-directed” nasal balloon system.
Broad claims that “all others are non-directional” are not the same as comparative clinical proof.
What experimental work suggests (and its limits)
Experimental analyses have discussed balloon motion that is less guided. [4] Such work can help explain mechanics, but it does not answer the bigger clinical question: which approach leads to better symptoms, airflow, safety, and durability over time. That requires comparative studies with consistent, long-term outcomes, not just device-mechanics discussions.
Summary: “Directional vs radial” is a design distinction; comparative clinical superiority has not been established.

How ClearPath Differs From Traditional Septoplasty (Procedure, Not Just Device)
Traditional septoplasty (high level)
Traditional septoplasty commonly involves elevating mucosal flaps to access the septum and then cutting, removing, or reshaping cartilage and or bone as needed to improve alignment and airflow.
ClearPath’s intended approach in selected cases
Authors describing ClearPath report a technique that aims to mobilize and reposition certain deviation patterns while, in selected cases, limiting the extent of flap elevation or tissue removal compared with some traditional approaches. These are technique goals, not proven advantages across all cases. [3]
Important boundaries
The same report notes that this device or technique may not address cartilaginous septum issues or septal spurs. These are examples, not a complete list, and were reported as reasons a clinician might choose another technique. [3]
Summary: ClearPath is a different procedural strategy that may limit dissection in selected cases, but it is not a universal replacement for traditional septoplasty.

What the Clinical Evidence Shows So Far (and What It Doesn’t)
Study design and cohort
A 2026 single-center retrospective series reported outcomes in 107 consecutive patients who underwent “force-directed” balloon-assisted septoplasty using ClearPath. Of these, a CT subgroup included 23 patients with pre- and postoperative scans, and SNOT-22 symptom scores at one month were available for 43 of 107 patients. This study design can be informative early on but does not establish superiority over other techniques. Outcomes were not available for the full cohort. [3]
CT alignment (imaging) findings
In the CT subgroup (n=23), the authors reported imaging symmetry changes at specific landmarks. [3]
About 22% improvement at the nasolacrimal duct (p=0.0047). About 45% improvement at the point of maximal deviation (p=0.0038).
A Wilcoxon signed-rank test indicated significant changes across measured landmarks. These data are imaging findings in 23 of 107 patients; they are not direct measures of symptom relief or airflow.
Who improved (within that CT subgroup)
At the point of maximal deviation, 78% (18 of 23) had at least a 30% improvement on the study’s imaging symmetry metric, and none in this subgroup were reported as worsened on that imaging metric. This small, retrospective subset cannot rule out the possibility of worsening in broader practice. [3]
Symptom improvement (SNOT-22 at one month)
Among the 43 patients with one-month SNOT-22 data, mean scores changed from 58.7 to 44.8—a 13.9-point drop (about 24%; p=0.02). Missing data can bias results, and a mean score of 44.8 can still reflect substantial symptoms. Statistical significance at the group level does not ensure individual benefit or superiority to other approaches. [3]
Safety signals reported (with limitations)
In this retrospective series, the authors reported no septal perforation, hematoma, mucosal injury, infection, synechiae, or conversion to traditional septoplasty. “None reported in this series” does not mean the risks are zero; a single retrospective report cannot define complication rates across settings. [3]
Honest limitations to keep in mind
This study had no control group, limited follow-up, and retrospective data collection. It does not identify which deviation patterns benefit most, does not establish long-term durability, and does not prove superiority versus other techniques. These are questions for future prospective, comparative research. [3]
Summary: Early retrospective data show imaging changes and short-term symptom shifts in subsets, but they are not proof of long-term or comparative superiority.

Questions to Raise With a Clinician
General considerations
A “force-directed” nasal balloon approach is typically considered when a clinician believes a deviation may be amenable to targeted repositioning—especially when the clinical goal is to focus correction at a particular problem area such as the point of maximal deviation. Whether that applies in a given case requires an in-person exam and, when appropriate, imaging. [3] For general background, see best candidates for balloon septoplasty with ClearPath: https://www.clearpathnasal.com/blog/best-candidates-for-balloon-septoplasty-with-clearpath
Boundaries noted in the literature
The cited report describes examples—such as cartilaginous septum problems or septal spurs—as potential reasons a clinician may select a different technique or a combined approach. This is not a complete list and should not be used for self-triage. [3]
Conversation starters for your visit
How would you describe my deviation pattern and its location? Do I have features like septal spurs or primarily cartilaginous deviation? Which outcome measures will you use—symptom scores such as NOSE or SNOT-22, imaging, or airflow testing—and on what follow-up timeline?
Summary: Only an examining clinician can decide candidacy; use questions to understand options, measurements, and follow-up.
Safety and Recovery: What Patients Typically Want to Know
What “minimally invasive” is aiming for
“Minimally invasive” here describes a design and technique goal in selected cases—less tissue disruption—not “no procedure” and not “no risk.” Whether any given case involves less dissection or quicker recovery depends on anatomy, technique, and clinical judgment. [3]
Known risks still exist
Any intranasal procedure can involve risks such as bleeding, infection, pain, scarring or adhesions, or need for revision. A balanced overview can be found here: septoplasty risks (what patients should know) https://www.clearpathnasal.com/blog/septoplasty-risks-what-patients-should-know. Device design discussions do not replace individualized risk–benefit counseling.
Why device design discussions don’t replace clinical outcomes
Directional force is an engineering concept; what ultimately matters is symptoms, airflow, safety, and durability over time. High-quality outcomes—especially longer follow-up and head-to-head comparisons using standardized measures—are needed to clarify where this strategy fits. [2,3]
Summary: “Minimally invasive” is a goal, not a guarantee; discuss risks, benefits, and follow-up plans specific to your case.
Bottom Line: ClearPath Is Designed to Direct Force—And More Comparative Research Is Needed
What can be said with confidence
ClearPath is a device with a balloon-and-spatula configuration intended to direct and limit force toward a targeted septal area. In that sense, it is accurately described—by manufacturer and authors—as a “force-directed” nasal balloon system. [1,2]
What should not be claimed on current evidence
It is not established that other balloons are uniformly “non-directional” in real-world outcomes, nor that ClearPath is clinically superior for every patient and deviation type. Early findings are encouraging but limited by retrospective design, missing data, and short follow-up. [2,3]
What to ask next
At a consultation, ask a qualified ENT which options, if any, fit the exam and imaging findings; how they measure results (symptoms, imaging, airflow); and what the expected follow-up timeline looks like. For additional background on the targeted-anatomy concept, see point of maximal deviation: https://www.clearpathnasal.com/blog/how-clearpath-addresses-point-of-maximal-deviation and how the ClearPath Nasal Balloon works (step-by-step): https://www.clearpathnasal.com/blog/how-the-clearpath-nasal-balloon-works-a-step-by-step-guide
Summary: ClearPath aims force at a chosen spot on the septum; stronger, comparative studies are needed to define where it performs best.
References
1. ClearPath Nasal Balloon System. Manufacturer website and comparison content. https://www.clearpathnasal.com/ (Manufacturer information is descriptive and should not be treated as clinical evidence.)
2. Brenner MJ, et al. New Medical Device and Therapeutic Approvals in Otolaryngology: State of the Art Review 2020. OTO Open. 2021. https://aao-hnsfjournals.onlinelibrary.wiley.com/doi/10.1177/2473974X211057035
3. Dillard J, Koudouovoh C, Lee V, Barnes C, Su R, Fortson JK. Outcomes of force-directed balloon-assisted endoscopic septoplasty: a retrospective analysis with a new technique and device. Rhinology Online. 2026;9:18-23. https://www.rhinologyonline.org/Rhinology_online_issues/manuscript_2530.pdf
4. Dillard J, et al. Balloon Dilation in Septal Surgery: An Experimental Analysis of Unguided Balloon Motion. 2025. https://urfpublishers.com/journal/case-reports/article/view/balloon-dilation-in-septal-surgery-an-experimental-analysis-of-unguided-balloon-motion
This article is for educational purposes only and is not medical advice. Please consult a qualified healthcare provider for diagnosis and treatment.

Dr. David G. Dillard
Author
Share it with others!