ClearPath for Severe Septal Deviation: When It May Help and What the Evidence Suggests
Severe septal deviation can significantly limit airflow and affect sleep and quality of life. Many people assume “severe” always requires more invasive surgery—but in selected cases, newer techniques may offer meaningful improvement with less tissue disruption. Estimates suggest over 250,000 septoplasties are performed each year in the U.S.
If you’re researching ClearPath for severe septal deviation, the key questions aren’t just “Can it work?”—they’re when it can work well, what “severe” means anatomically, and which outcomes have actually been measured.
A helpful frame is: “Severe” describes the size and location of the roadblock, but the best solution depends on what kind of roadblock it is. Some blockages are best handled with full reconstruction; others can improve with targeted realignment.
What counts as a “severe” deviated septum?
Severity isn’t just a feeling—it’s anatomy plus airflow
A deviated septum means the wall between the nostrils (the septum) is off-center. “Severe” typically refers to how much and where the septum bends—especially when it creates a tight bottleneck that reduces airflow through one or both sides of the nose.
Symptoms and imaging don’t always match. Some people show striking deviation on imaging but report mild symptoms; others feel severely blocked even when the picture looks less dramatic. That’s why ENTs integrate your symptom history, nasal exam, and sometimes CT imaging when discussing options. The goal isn’t a “perfectly straight septum on paper,” but a clearer airway in real life—especially at night, during exercise, or when allergies flare.
Key areas ENTs look at (plain-language definitions)
Two common CT landmarks help clinicians describe where the septum is most off-center and to track change after a procedure: Point of Maximal Deviation (PMD): the spot where the septum is farthest off-center—often the tightest point driving blockage. Nasolacrimal duct (NLD) level: a consistent reference level on imaging that makes it easier to compare alignment changes across patients. For a deeper look at definitions and landmarks, see “how severity is measured.” https://www.clearpathnasal.com/blog/how-severe-is-your-deviation-understanding-the-measurement
Summary: Improving how air moves matters more than making a scan look perfect.

Why traditional septoplasty can be effective—but also more involved
What “traditional” approaches often require
Traditional septoplasty can be highly effective, particularly for complex anatomy. Depending on the case, it may involve lifting the lining over the septum (flap elevation), reshaping or removing segments contributing to blockage, and stabilizing the septum with sutures and/or packing.
Because it’s more tissue-involving, informed-consent discussions typically include risks such as bleeding, perforation, scar bands (synechiae), or prolonged congestion during recovery. For some patients, that “more involved” tradeoff is exactly what’s needed—especially with rigid spurs, complex bends, or multiple structures contributing to obstruction. For others, the question becomes whether you can get meaningful improvement with less cutting, lifting, and removal.
Summary: Traditional septoplasty remains the right choice for certain anatomic patterns—especially when multiple structures or rigid spurs are the main issue.

How ClearPath works (and why the mechanism matters in severe deviations)
The core idea—controlled mobilization instead of extensive cutting
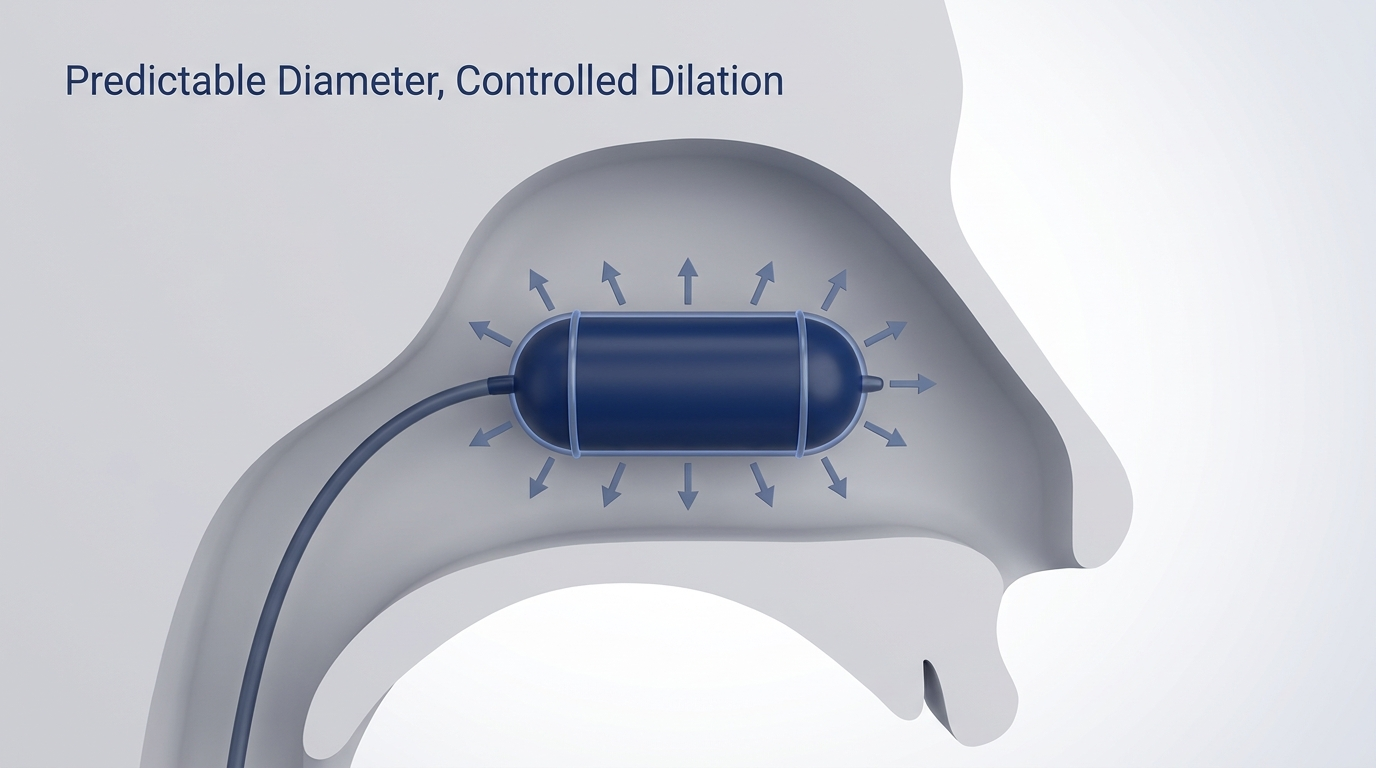
ClearPath is a device-based, balloon-assisted, endoscopic septoplasty technique. The concept is to mobilize the bony septum using targeted, controlled force—rather than relying primarily on broad cutting or removal. In the described technique, the ClearPath Nasal Balloon Catheter system pairs a force-directed instrument (spatula) with a high-pressure, noncompliant balloon to mobilize bony septum while distributing pressure. In the reported series, flap elevation, sutures, and packing were reduced or avoided in appropriate cases; your surgeon will determine if that applies to your anatomy.
Important context: Although “minimally invasive,” it is still a procedural surgical intervention performed endoscopically; risks and recovery vary by patient and technique. Regulatory note: the device has FDA 510(k) clearance (K202857). Clearance indicates the device was found substantially equivalent to a predicate for market clearance; it does not, by itself, prove clinical superiority.
If traditional septoplasty is sometimes like renovating a wall to widen a hallway, ClearPath’s concept is more like strategically nudging the wall where it’s pinching the passage—when the anatomy allows.
Why “force-directed” matters for severe deviations
Severe deviations aren’t uniform. One segment may be much more resistant than another, and the tightest point can dominate symptoms. A force-directed, localized approach aims to focus correction where the airway is tightest (often near the PMD), avoid unnecessary disruption to areas that aren’t driving obstruction, and enable stepwise improvement rather than treating every segment the same. For more on targeting the tightest point, see how ClearPath addresses the point of maximal deviation (PMD). https://www.clearpathnasal.com/blog/how-clearpath-addresses-point-of-maximal-deviation
What a patient experiences (high level)
While specifics vary by clinician and anatomy, the typical flow includes consultation and a nasal exam (some surgeons also use CT based on symptoms and preference), an endoscopic procedure with targeted septal mobilization, and recovery focused on gradually improving breathing as swelling settles (timing of relief varies by person). Summary: The technique is designed to apply focused mechanical correction where it matters most, with the intent to minimize unnecessary tissue disruption when appropriate.

What the clinical evidence says about ClearPath in severe deviations
Study design matters
The main outcomes published to date come from a single-arm, retrospective series. That design can show feasibility and short-term outcomes but cannot prove head-to-head superiority over traditional septoplasty.
Safety outcomes in a real-world series
In a retrospective analysis of 107 consecutive balloon-assisted septoplasty cases using ClearPath, the authors reported no major complications (no septal perforation, hematoma, mucosal injury, infection, synechia, or conversion to traditional septoplasty). Because this was a single-arm retrospective series, absence of reported events does not mean zero risk for all patients or settings.
Objective alignment improvements on CT (including severe cases)
Among the 23 patients with paired pre- and post-procedure CT scans, mean septal symmetry improved 22% at the NLD and 45% at the PMD (both p = 0.005). Seventy-eight percent (18/23) achieved at least 30% improvement; no patient in this paired-CT subset worsened. The authors reported approximately 45% improvement for severe septal deviations when stratified by severity; details of severity criteria and subgroup size are defined in the study methods. The largest average change overall was at the PMD, aligning with the “target the tightest point” rationale.
Patient-reported symptom improvement (quality of life)
Among patients who completed SNOT-22 questionnaires (n = 43), mean scores improved from 58.7 to 44.8 at one month (23.8% reduction, p = 0.02). This is a short-term, single-arm result without a randomized comparator, and some patients may still report meaningful symptom burden at these scores.
What these results do—and don’t—prove
Retrospective, single-arm design means not randomized or controlled. Only 23 patients had paired CT scans. Symptom follow-up in the report was short (one month). Bottom line: The series supports promising, anatomy-targeted outcomes for selected patients—including some with severe deviations—but larger, longer, and comparative studies would strengthen the evidence. Summary: Early data suggest targeted alignment gains and symptom improvements in selected cases, with important limits due to study design and sample size.

Why ClearPath can be helpful even when the deviation is “severe”
“Severe” can reflect many anatomic patterns—bend location, rigidity, presence of spurs, turbinate enlargement, or valve narrowing. ClearPath may be especially compelling when obstruction is driven by septal displacement at key landmarks (like the PMD) that can be improved through targeted mobilization. Two people can both be told they have “severe deviation,” yet one may have a single dominant choke point while the other has multiple structural contributors (septum plus valve plus turbinates). The first pattern may fit a targeted approach; the second may require a broader plan. Summary: The match between your anatomy and the device’s mechanism is the key predictor—not the word “severe” alone.

When a severe deviation may need traditional septoplasty (or additional procedures)
Examples where additional approaches may be required
Complex bony deformities or spurs that require resection; significant nasal valve collapse (a structural support problem); severe turbinate hypertrophy needing turbinate reduction; revision cases with scarring (case-by-case); combined functional and cosmetic goals (often part of broader nasal surgery). For a side-by-side context on approaches, see ClearPath vs traditional septoplasty to compare recovery, safety, and results. https://www.clearpathnasal.com/blog/clearpath-vs-traditional-septoplasty-recovery-safety-results Summary: Some severe patterns need reconstruction or adjunctive procedures beyond septal mobilization.
Who is a good candidate for ClearPath in severe deviations?
Examples your ENT may consider—not a self-screening tool
Persistent nasal blockage despite appropriate medication when the cause is structural; a deviation pattern that appears amenable to targeted mobilization; preference to avoid packing/sutures when clinically appropriate. Learn more about who is a good candidate for ClearPath in the guide to best candidates for ClearPath balloon septoplasty. https://www.clearpathnasal.com/blog/best-candidates-for-balloon-septoplasty-with-clearpath
Common reasons to consider other options
Obstruction is strongly multi-factor and the septum is only part of the problem; expectations center on a perfectly straight septum rather than functional improvement; the nose requires extensive structural reconstruction beyond septal alignment. Summary: Candidacy depends on detailed anatomy, goals, and clinician judgment.
What results should patients realistically expect?
Improvements that matter day-to-day
Realistic goals focus on function and quality of life, such as easier nasal breathing (especially at night), less congestion and facial pressure, and better sleep quality (consistent with SNOT-22 domains reported in the series). Timing expectations help: many patients notice changes gradually as swelling resolves, not instantly.
What “success” looks like clinically
Success blends symptom improvement (e.g., via SNOT-22 or similar tools), objective alignment change when CT is used (e.g., PMD/NLD symmetry), and a follow-up plan if symptoms persist. Summary: Success blends how you feel, what changes are seen, and clear next steps if you need more improvement.
FAQs
Can ClearPath treat a severely deviated septum?
It may help in selected severe deviation patterns—particularly when a correctable septal displacement at key points is driving obstruction. Candidacy depends on your specific anatomy and other contributors to blockage.
Is ClearPath safer than traditional septoplasty?
Comparative safety has not been established in a randomized head-to-head trial. In one single-arm, retrospective series (n = 107), the authors reported no major complications. Individual risk varies by anatomy, technique, and medical history. For a broader context, see ClearPath vs traditional septoplasty. https://www.clearpathnasal.com/blog/clearpath-vs-traditional-septoplasty-recovery-safety-results
How do doctors measure improvement?
Symptom scoring (e.g., SNOT-22) and imaging-based symmetry at landmarks such as the PMD and NLD (when CT is used). For background on what severity means and how it’s measured, see understanding deviation severity measurements. https://www.clearpathnasal.com/blog/how-severe-is-your-deviation-understanding-the-measurement
What if ClearPath doesn’t fully fix my breathing?
If symptoms remain, an ENT typically reassesses what’s still limiting airflow (septum versus turbinates versus valve) and discusses next-step options. Plans are individualized to the residual cause of obstruction.
Conclusion—the takeaway for patients with “severe deviation”
ClearPath’s role in severe cases is conditional: it’s most promising when your obstruction matches what the device is designed to address—targeted septal mobilization at dominant problem points. Think of it as a potential alternative to traditional septoplasty for the right anatomy, not a one-size-fits-all replacement. Talk with your ENT about how they would measure success in your case (symptoms, airflow, and/or CT landmarks).
Citations
Dillard J, Koudouovoh C, Lee V, Barnes C, Su R, Fortson JK. Outcomes of force-directed balloon-assisted endoscopic septoplasty: a retrospective analysis with a new technique and device. Rhinology Online. 2026;9:18–23.
U.S. Food & Drug Administration. 510(k) Summary K202857 (ClearPath Nasal Balloon Catheter). 2021. https://www.accessdata.fda.gov/cdrh_docs/pdf20/K202857.pdf
ClearPath Nasal (product/technology context): https://www.clearpathnasal.com
This article is for educational purposes only and is not medical advice. Please consult a qualified healthcare provider for diagnosis and treatment.

Dr. David G. Dillard
Author
Share it with others!