Avoiding the “Open” Septoplasty Technique
Septoplasty is surgery to straighten the nasal septum—the wall of cartilage and bone that divides the left and right nasal passages. When the septum is significantly deviated, airflow can drop on one or both sides, contributing to nasal obstruction, mouth breathing, snoring, poor sleep quality, and reduced exercise tolerance. Septoplasty is commonly performed to improve nasal breathing and quality of life [1][2].
It’s also very common for patients to ask about avoiding the open septoplasty technique. The concerns usually fall into two buckets:
- A visible scar (even a small one)
- The perception of a “bigger” operation with more swelling or downtime
Those concerns are understandable. In many cases, a surgeon can correct a deviation without any external incision. But just as importantly: avoiding an open approach isn’t always the best—or safest—choice for long-term breathing and structural stability [1][2]. If you’re weighing downtime, you may find this helpful: recovery time for septoplasty.
(This article is educational and not a substitute for personal medical advice.)
What “Open” vs “Closed” Septoplasty actually means
“Closed” (endonasal) septoplasty—no external incision
A closed (endonasal) septoplasty is performed entirely through incisions inside the nostrils. Because the cuts are internal, there is no visible external scar [1][2].
Many surgeons also pair a closed approach with a small camera for visualization—this is often called endoscopic septoplasty. Endoscopic viewing can improve precision, especially when the working space is narrow or the deviation is more posterior (farther back in the nose) [1][2].
In practical terms: closed/endonasal (with or without endoscopy) can be a great fit when the “problem area” is reachable and correctable from inside the nose without extensive structural rebuilding. For a deeper comparison of pros and cons, see endoscopic septoplasty vs open surgery.
“Open” septoplasty—added incision for visibility and access
An “open” approach typically includes a small columellar incision (across the strip of skin between the nostrils). This allows the nasal skin and soft tissue to be lifted so the surgeon can see and access the underlying cartilage and bone more directly [1][2].
Open exposure is commonly chosen when:
- The deviation is complex
- The front of the septum (support area) needs more controlled work
- Septoplasty is being combined with rhinoplasty for structural or cosmetic reasons [1][2]
When combined aesthetic and functional goals are on the table, septoplasty and cosmetic rhinoplasty can be combined.
Key point: open surgery isn’t “better” by default—it’s a tool. In challenging anatomy, it can make certain corrections more controlled and stable.
Bottom line: open and closed are tools—the right choice depends on what needs to be fixed and how much support must be preserved.

When avoiding an open septoplasty is often feasible
Deviations that can be corrected through internal access
Avoiding the open septoplasty technique is often realistic when the septal deviation can be corrected using internal incisions alone—without needing extensive reconstruction of the nose’s support structures [1][2].
A surgeon may be able to keep things endonasal or endoscopic when:
- The deviated portion is accessible through intranasal incisions
- The correction can be done while maintaining critical support (more on that below)
- There isn’t a major external nasal deformity that also needs structural correction [1][2]
A concrete example: if the main bend is farther back or higher inside the nasal cavity, it may be well-suited to endoscopic visualization and targeted correction. On the other hand, a pronounced deviation right at the front “entry” of the nose can be harder to stabilize through a narrow internal corridor.
What the evidence says about outcomes in selected cases
Studies comparing approaches suggest that, in selected patients, functional outcomes of endonasal or endoscopic septoplasty can be comparable to open approaches [3][4]. A systematic review and meta-analysis found endoscopic techniques can provide strong symptom improvement, with some potential advantages in visualization and targeted correction [4].
Patient takeaway: in experienced hands, a closed or endoscopic approach can work very well—even for some harder deviations—when you’re the right candidate [3][4].
In the right anatomy, many deviations can be safely corrected without an external incision.

The non-negotiable principle—protecting the septal “L-strut”
What the L-strut is and why patients should care
No matter which technique is used, one principle matters enormously: L-strut preservation.
The septal “L-strut” is the L-shaped portion of cartilage that supports:
- The nasal bridge (dorsum)
- The nasal tip (caudal support)
A helpful analogy: think of the L-strut like the load-bearing corner of a door frame. You can trim or reshape material around it, but if you weaken that corner too much, the structure can shift—affecting both appearance and function. The goal of septoplasty is better breathing without weakening support [1][2].
Typical safe dimensions surgeons try to preserve
Many surgical protocols emphasize preserving an L-strut that is roughly 10–15 mm wide along both the dorsal (top) and caudal (front or bottom) segments to reduce the risk of collapse or a saddle-nose deformity [1][2].
This is one reason technique choice matters: if a deviation involves the support zone, the surgeon may need more access—and more reconstruction options—to keep the nose stable.
Stable breathing gains depend on protecting the L‑strut’s structural support.

The main reason “open” still matters—access for complex deviations
Deviations that are harder to fix through a closed approach
Even when someone strongly prefers no external incision, there are situations where avoiding open exposure can make the correction less predictable.
Open exposure may be the safer or more reliable option when the deviation is:
- Severe caudal (a caudal septal deviation affects the front or bottom support area)
- Very anterior (close to the nostrils)
- Complex (S-shaped or twisted across multiple planes)
- Involving the L-strut itself, where stabilization or reconstruction may be required [1][5]
A clinician-style way to summarize it is: if the support is crooked, not just the airway, you may need more than a limited internal approach. The priority is durability—straightening that holds up over time and doesn’t trade obstruction for instability.
When grafting or reconstruction is more likely
For severe or unstable deviations, surgeons may consider methods such as:
- Cutting-and-suture techniques
- Swinging-door technique
- Batten grafts
- Extracorporeal septoplasty, where the septum is rebuilt outside the nose and then re-implanted for stability [1][5]
These advanced reconstructions often benefit from open (or extracorporeal) exposure so the surgeon can align structures accurately and secure them reliably [1][5].
When the support is crooked, open exposure often makes a lasting, stable repair more predictable.
Endoscopic/endonasal approaches: benefits—and realistic tradeoffs
Potential benefits patients often experience
When you’re a good candidate, endonasal or endoscopic septoplasty can offer appealing advantages:
- No external incision or scar
- Potentially less dissection depending on the specific technique
- Efficient, targeted correction with endoscopic visualization in selected cases [4]
These benefits are a major reason patients ask about avoiding the open septoplasty technique in the first place—especially if they want to minimize visible signs of surgery.
The key limitation: a narrower working space
The tradeoff is access. A closed or endoscopic approach gives the surgeon less room to manipulate cartilage and bone. In some noses, that narrow working space can make it harder to:
- Fully correct complex bends at the very front of the septum
- Address shape or support issues that influence the outer nose [1][2]
In plain terms: it’s a bit like repairing a bent support beam through a small access hatch—sometimes it’s enough, and sometimes you need a wider view to do a stable repair.
A note on evidence quality (simple but honest)
It’s also worth knowing that many studies comparing open vs endoscopic or endonasal approaches are nonrandomized, and the choice of technique often depends on patient anatomy and surgeon preference or experience. That means outcomes can be influenced by selection bias (for example, harder cases being sent to one approach more often) [3][4].
Closed or endoscopic can be less invasive, but access limits may cap what can be safely corrected.
“Difficult deviation” cases—can closed/endoscopic still work?
What one study found (in accessible language)
A study examining 60 patients with “difficult” deviations—including S-shaped, multiple, and high deviations—found that endonasal septoplasty improved function similarly to open septoplasty in that setting [3].
This supports an important nuance: even some challenging anatomy may still be managed without open exposure when the deviation is reachable, the plan protects support structures, and the surgeon is comfortable with endonasal or endoscopic methods.
Why that doesn’t mean closed is always best
That same study was nonrandomized, and approach choice was influenced by factors like surgeon experience and patient preference [3]. So it shouldn’t be interpreted as closed is always better—only that closed or endoscopic options can still be effective for selected difficult cases.
Even some “difficult” deviations can be managed endonasally—selection and surgeon experience are key.
A minimally invasive option patients may hear about: balloon-assisted septoplasty (CNB)
What balloon-assisted septoplasty is trying to do
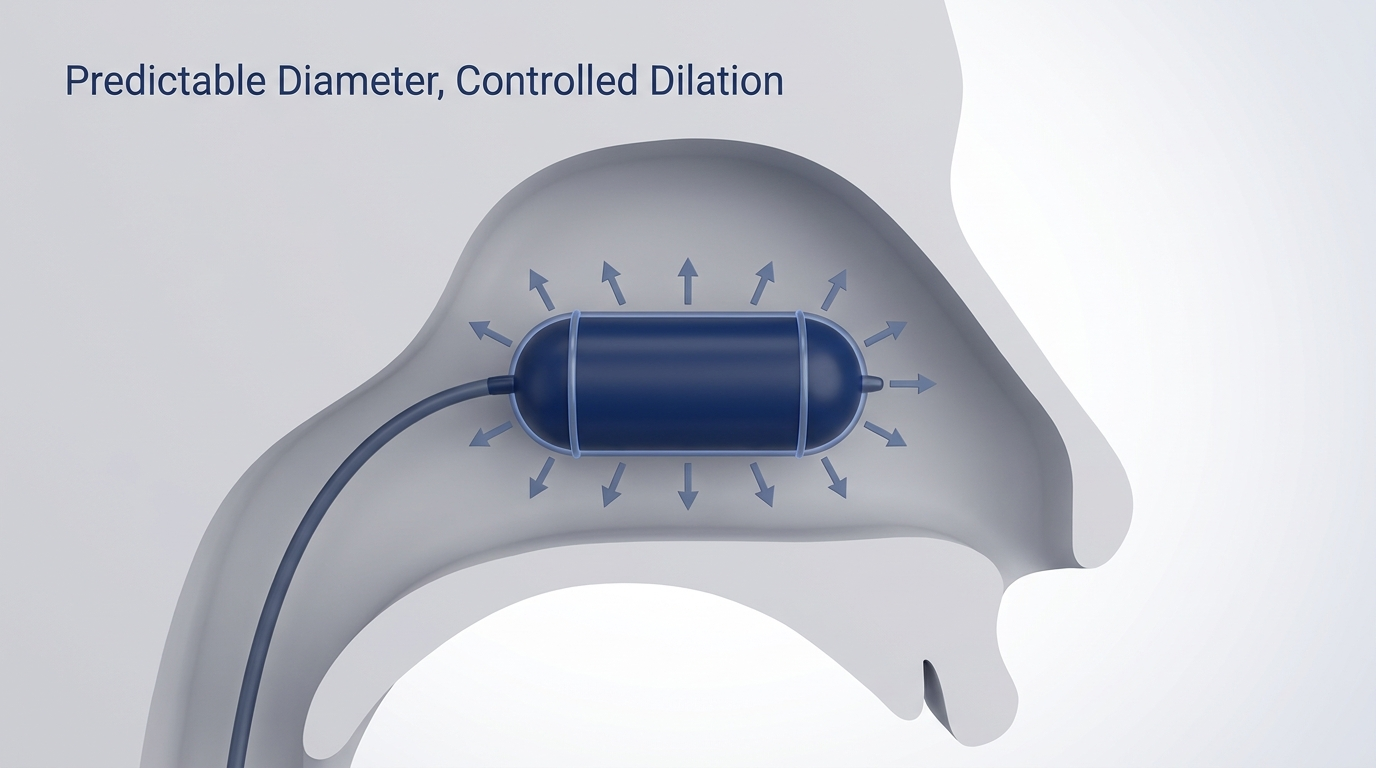
Balloon-assisted septoplasty is an approach intended to mobilize certain bony deviations using endoscopic guidance with a force-directed balloon and shaped instrument, with the goal of reducing or avoiding extensive flap elevation, packing, and prolonged anesthesia compared with traditional septoplasty approaches [6]. For a quick primer, see what balloon-assisted septoplasty is.
One example is the ClearPath Nasal Balloon (CNB)—a device used as part of this balloon-assisted septoplasty concept [6]. In that sense, ClearPath may be discussed as an alternative to more traditional septoplasty methods for appropriately selected anatomy.
Early outcomes and what they may mean for patients
In a retrospective report of CNB outcomes:
- Safety (107 cases): No major complications were reported (including no septal perforation, hematoma, synechia, or conversion) [6].
- CT alignment (subset n=23): On coronal CT, mean maximal deviation from the midline decreased by 45%, and deviation near the nasolacrimal duct decreased by 22% (p=0.005) [6].
- Symptoms (subset n=43): SNOT-22 scores improved from 58.7 to 44.8 at 1 month (a 23.8% reduction; p=0.02), with notable gains in congestion, facial pressure or headache, and sleep quality [6].
Important limitations to mention (build trust)
These findings are early and should be viewed in context: the study was retrospective, only a subset had CT comparison, and more prospective research is needed [6].
If you’re exploring whether you’re a candidate for a minimally invasive option, you may find this helpful: best candidates for balloon septoplasty.
Balloon-assisted septoplasty is an emerging, minimally invasive option for select anatomies; evidence is early and evolving.

How to decide: a patient checklist for choosing the right approach
Questions to ask your ENT surgeon
If you’re focused on avoiding the open septoplasty technique, the most productive next step is to ask targeted anatomy-based questions:
- Where is my deviation—front (caudal or anterior) or back (posterior)?
- Is my L-strut involved?
- Do I need grafting or reconstruction?
- Is there any external nasal deformity affecting breathing or appearance?
- How often do you perform closed (endonasal) septoplasty, endoscopic septoplasty, and open septoplasty?
- What is your plan if you find more complex anatomy during surgery? [1][2]
If you’re interested in minimally invasive options, it’s reasonable to ask your local ENT whether something like balloon-assisted septoplasty (including ClearPath, where appropriate) is an option for your specific deviation pattern—and why or why not.
Also consider reviewing typical downtime and aftercare so you can plan realistically: recovery time for septoplasty.
Reframe the goal: function first, scar second
A scar-avoiding mindset is understandable—but the best approach is the one that delivers a durable breathing improvement while maintaining stable support.
In other words, the decision should be guided by:
- Exact deviation location and severity
- Whether the caudal septum or L-strut needs reconstruction
- Whether additional structural work is needed
- Surgeon experience with the technique you’re considering [1][5]
Choose the approach that maximizes durable function and stability for your specific anatomy.

Conclusion: Avoiding “open” septoplasty can be possible—when it’s the right match
Avoiding the open septoplasty technique is often achievable when a deviation can be corrected through internal nasal incisions with careful L-strut preservation. In appropriate candidates, closed (endonasal) septoplasty and endoscopic septoplasty can deliver strong functional results [1][4].
However, severe caudal septal deviation, very anterior bends, complex multi-plane deformities, or deviations involving the L-strut may still require open exposure or more advanced reconstruction (including extracorporeal septoplasty) for the most stable outcome [1][5].
CTA: If you’re considering septoplasty, schedule an evaluation with your local ENT so they can pinpoint the deviation location (often with nasal endoscopy and or imaging when appropriate) and walk you through which approach best matches your anatomy and goals—including whether a minimally invasive alternative like balloon-assisted septoplasty (such as ClearPath, if available and appropriate) is worth discussing [1][4][5].
Avoiding an open approach is often possible—but long-term breathing and support come first.
References
[1]: University of Iowa Head and Neck Protocols. Septoplasty for Nasal Obstruction: Indications and Techniques (2023). https://iowaprotocols.medicine.uiowa.edu/protocols/septoplasty-nasal-obstruction-indications-and-techniques
[2]: StatPearls/NCBI Bookshelf. Septoplasty (2022). https://www.ncbi.nlm.nih.gov/books/NBK567718/
[3]: Eliçora SS, et al. Difficult Septal Deviation Cases: Open or Closed Technique? (2017). https://www.sciencedirect.com/science/article/pii/S1808869416300593
[4]: Hong CJ, et al. Open versus Endoscopic Septoplasty Techniques: A Systematic Review and Meta-analysis (2016). https://pubmed.ncbi.nlm.nih.gov/28124656/
[5]: Bogari A, et al. Current Practices and Evidence in Caudal Septoplasty (2025). https://academic.oup.com/asjopenforum/article/doi/10.1093/asjof/ojaf170/8384000 and overview: https://pmc.ncbi.nlm.nih.gov/articles/PMC8520545/
[6]: Dillard J, et al. ClearPath Nasal Balloon (CNB) septoplasty outcomes (2026). Rhinology Online 2026;9:18–23. doi:10.4193/RHINOL/25.018.
This article is for educational purposes only and is not medical advice. Please consult a qualified healthcare provider for diagnosis and treatment.

Dr. David G. Dillard
Author
Share it with others!